How to Breastfeed: Step-by-Step Latch and the Best Positions
By Breastfeeding Mom Editorial TeamUpdated 6 min read

Learning how to breastfeed takes practice, for you and for your baby. Most of what makes feeding comfortable and effective comes down to two things: how you hold your baby (positioning) and how your baby takes the breast into their mouth (the latch, which the NHS calls attachment).
This guide takes you through the latch step by step, compares five common positions, and lists the beginner mistakes that are easiest to fix. If you’re new to all of this, our overview of breastfeeding basics explains how milk supply works and what the first weeks look like.
Before you start
- Watch for early hunger cues. Hands to the mouth, turning toward the breast, lip smacking or licking. Crying is a late sign, and a frantic baby finds it harder to latch.
- Get comfortable. Sit or recline with your back supported and your shoulders relaxed. Use pillows to bring your baby up to you so you don’t hunch over.
- Undress your baby a little if they’re sleepy. Skin-to-skin contact helps keep newborns calm and alert enough to feed.
How to latch your baby, step by step
- Hold your baby close, facing you. Their head, shoulders and body should be in a straight line, tummy to your body, so they don’t have to turn their head to reach the breast.
- Line up nose to nipple. Start with your baby’s nose level with your nipple. Support their neck and shoulders, not the back of the head, so they can tip their head back.
- Wait for a wide-open mouth. Let your nipple brush their top lip. Most babies respond by opening wide, like a yawn.
- Bring baby to breast, chin first. As the mouth opens wide, move your baby onto the breast so the chin touches first and the lower lip lands well below the nipple. Bring the baby to the breast rather than leaning the breast into the baby.
- Check the latch. Your baby’s chin presses into the breast, the nose is clear, and the mouth is full of breast.
If your breasts are large, support the breast with your hand well back from the areola, or place a rolled towel under it so your baby’s mouth meets the nipple straight on.
Signs of a good latch
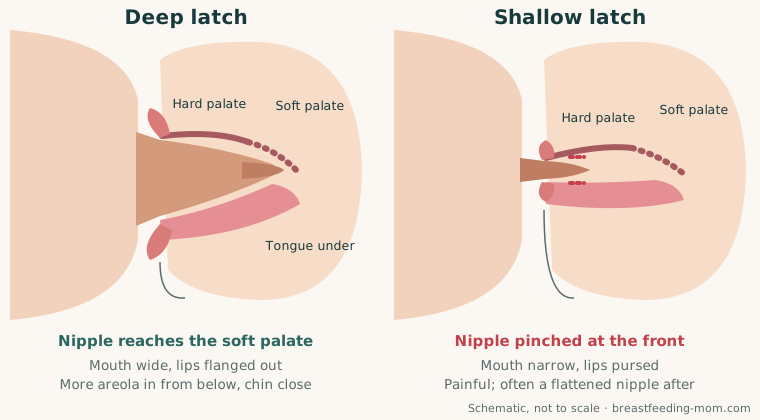
In a deep latch the nipple sits far back in your baby’s mouth, so it isn’t squeezed. In a shallow latch it’s pressed against the hard palate at the front, which is what makes feeding hurt.
- More of the darker skin around the nipple shows above your baby’s top lip than below the bottom lip
- Lips are flared outward, not tucked in
- Cheeks stay full and rounded, not dimpled or sucked in
- Your baby starts with quick sucks, then settles into longer, slower sucks with pauses
- You can hear or see swallowing
- It feels comfortable after the first few sucks
- Your baby comes off the breast on their own when finished, and your nipple looks the same shape as before, not flattened or creased
Breastfeeding positions compared
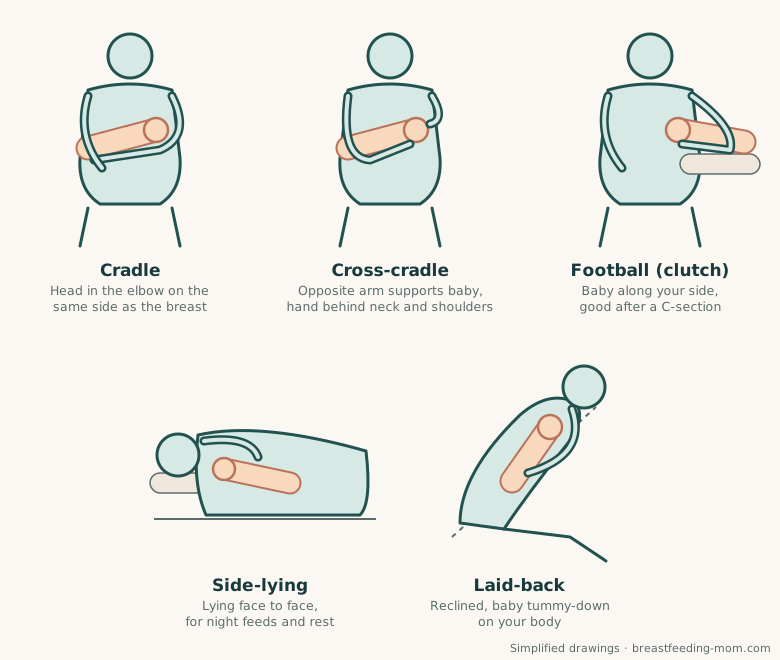
There is no single right position. Try a few and use whatever is comfortable for you and lets your baby latch deeply. Changing positions can also help if you have sore spots.
| Position | How it works | Good for |
|---|---|---|
| Cradle | Baby lies across your lap on their side, head in the bend of your elbow on the same side as the breast | Babies who latch well; older babies |
| Cross-cradle | The arm opposite the breast supports your baby, your hand behind the neck and shoulders | Newborns and babies who struggle to latch, since you have more control of the head |
| Football (clutch) | Baby tucked along your side under your arm, head at the breast, legs toward your back | After a C-section, twins, larger breasts, or a forceful let-down |
| Side-lying | You and your baby lie on your sides facing each other, with pillows behind your back and head | Night feeds, rest, recovery after birth |
| Laid-back | You recline semi-upright and your baby lies tummy-down on your body | Newborns, babies with a strong let-down or oversupply, and gentle early feeds |
The AAP notes that the laid-back position uses a baby’s natural instincts when they lie skin-to-skin on your chest, and Cleveland Clinic points out that it can slow a fast milk flow. If you feed lying down, place your baby on their back on a firm, flat sleep surface if you start to feel sleepy.

How to break the latch
Never pull your baby straight off the breast. The suction can hurt and damage your nipple. Instead, slide a clean finger into the corner of your baby’s mouth, between the gums, to break the seal. Then gently take your baby off and try again.
Break the latch and re-latch whenever it hurts beyond the first few sucks, when you hear clicking, or when your baby seems to be sucking on just the nipple.
Common beginner mistakes (and quick fixes)
- Leaning over your baby. You end up with a sore back and a shallow latch. Bring your baby up to you with pillows instead.
- Latching before the mouth is open wide. A small mouth means a nipple-only latch. Wait for that big yawn.
- Pushing the back of your baby’s head. Babies need to tip their head back to latch deeply. Support the neck and shoulders instead.
- Baby’s body turned away. If your baby has to turn their head, swallowing is harder. Bring them tummy to tummy.
- Watching the clock. Feeds vary in length. Let your baby set the pace.
- Waiting for crying. Offer the breast at early hunger cues for an easier latch.
- Putting up with pain. Pain is a signal to re-latch or get help, not something to push through. See our guide to sore nipples if your nipples are already tender or cracked.
Once you’ve got the latch, the next question is usually timing. Our guide on how often to breastfeed a newborn covers feeding frequency, cluster feeding and sleepy babies. If your breasts get very full and hard around days 2 to 5, that can make latching harder. Hand expressing a little milk first can help, and our guide to breast engorgement explains more.
When to call a doctor or lactation consultant
Get help from an IBCLC (International Board Certified Lactation Consultant), your midwife or your baby’s doctor if:
- Feeding is painful throughout most feeds, or your nipples are cracked, bleeding or look flattened or white after feeds
- You hear frequent clicking, or your baby keeps slipping off the breast
- Your baby is very sleepy, hard to wake for feeds, or seems unsatisfied after most feeds
- Your baby has fewer wet or dirty diapers than expected for their age
- You have a fever, or a red, painful area on your breast
Our breastfeeding support page lists where to find lactation consultants, La Leche League groups and helplines. Seeing someone watch a feed in person is often the fastest way to fix a latch.
Frequently asked questions
How long should each breastfeeding session last?
There is no set time, and feed length varies a lot from baby to baby and feed to feed. Watch your baby, not the clock: let them feed until they slow down, relax and come off on their own.
Should breastfeeding hurt?
Some tenderness in the first days is common, especially as your baby latches on. Pain that lasts through the feed, or nipples that look flattened, creased or cracked afterward, usually point to a shallow latch and are worth getting help with.
Do I need a nursing pillow?
No, but many parents find one helpful for bringing the baby up to breast height and resting their arms. Regular pillows or a rolled blanket work just as well.
What if my baby falls asleep at the breast?
Sleepy newborns often doze off mid-feed. Try gentle breast compression, stroking their cheek or feet, or switching sides to wake them up enough to keep feeding.
Sources
- NHS: Breastfeeding positioning and attachmenthttps://www.nhs.uk/baby/breastfeeding-and-bottle-feeding/breastfeeding/positioning-and-attachment/
- HealthyChildren.org (AAP): Positioning Your Baby for Breastfeedinghttps://www.healthychildren.org/English/ages-stages/baby/breastfeeding/Pages/Positioning-Your-Baby-for-Breastfeeding.aspx
- Cleveland Clinic: Breastfeeding Positionshttps://health.clevelandclinic.org/breastfeeding-positions/
- CDC: Signs Your Child Is Hungry or Fullhttps://www.cdc.gov/infant-toddler-nutrition/mealtime/signs-your-child-is-hungry-or-full.html
- NHS: Sore or cracked nipples when breastfeedinghttps://www.nhs.uk/baby/breastfeeding-and-bottle-feeding/breastfeeding-problems/sore-nipples/
This guide is general information, not medical advice. For your own situation, talk to your doctor, midwife, pharmacist or an IBCLC lactation consultant. Read our medical disclaimer and find breastfeeding support near you.
Related articles

Side-Lying Breastfeeding: How to Do It Safely
How to breastfeed lying on your side, step by step, who it helps most, how to switch sides, and what the AAP says about feeding in bed and safe sleep.

Breastfeeding Twins: Positions, Milk Supply and a Plan That Works
How to breastfeed twins: building enough milk, feeding together or one at a time, the best tandem positions, pumping for preterm twins and getting help.

Paced Bottle Feeding: How to Bottle Feed a Breastfed Baby
Step-by-step paced bottle feeding: how to hold your baby and the bottle, when to pause, how long a feed should take and the signs your baby is full.

Breastfeeding After a C-Section: First Feeds, Positions and Pain Relief
How to breastfeed after a C-section: skin-to-skin in the OR, comfortable positions that protect your incision, pain relief, and help if milk is slow.

Breastfeeding for Beginners: How It Works and What to Expect
How milk is made, what the first days look like, how to get a good latch and how to tell your baby is getting enough.